Early detection is shifting from symptoms to risk
It can feel almost suspicious to qualify for a test when nothing in your day-to-day life feels “wrong.” You climb stairs, you cough a little in the morning like you always have, and it’s easy to file that under normal wear-and-tear. But smoking history doesn’t fade out as neatly as symptoms do. Even after quitting, the risk can stay elevated for years, which is why screening is aimed at people who feel mostly fine.
That’s the quiet shift: early detection is less about waiting for a new problem and more about tracking a known risk over time. A low-dose CT isn’t looking for a single, obvious “yes or no” answer—it’s often measuring small changes that may or may not matter yet. This can create a strange middle ground: a scan can be “not concerning” and still not feel fully reassuring, because the point is to keep watching, not to declare the story over.
Why low-dose CT changed what “screening” means

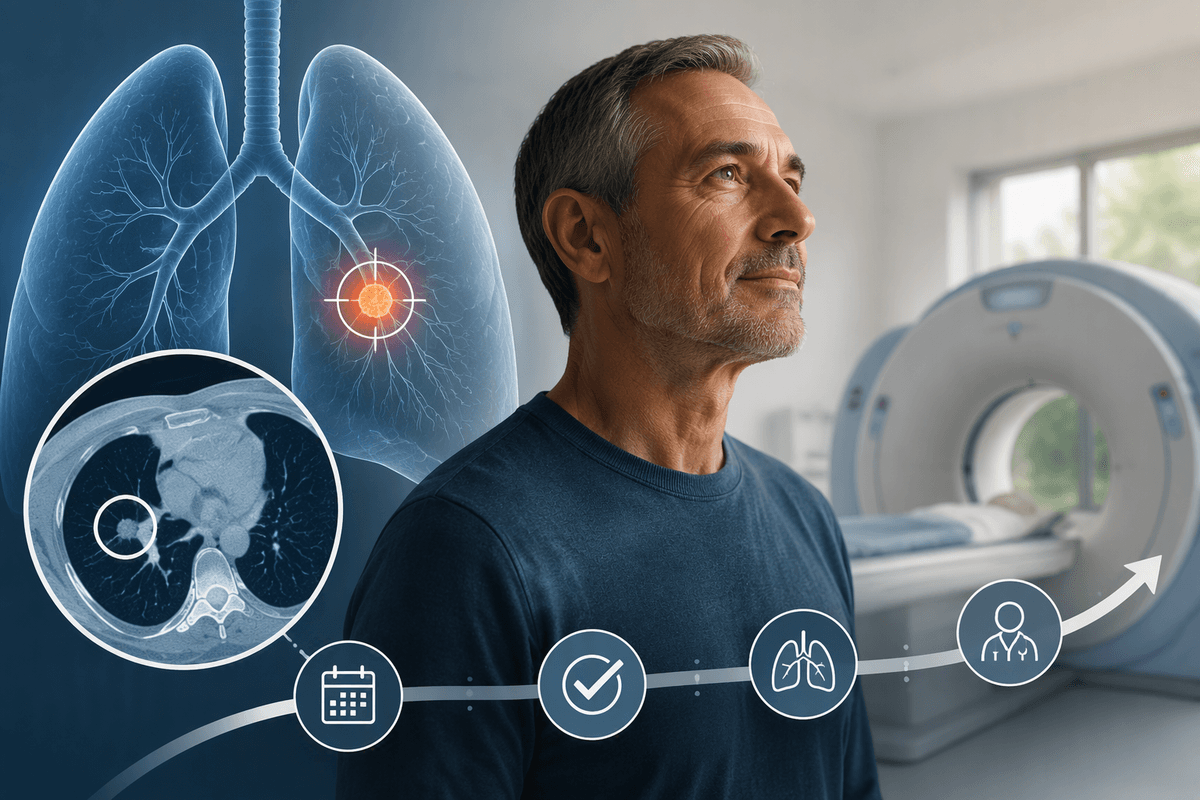
The first time you lie still in the scanner, the whole thing can feel almost too quick to count as “real” testing. No needles, no sedation, just a few minutes of holding your breath while a machine takes thin-slice pictures of your lungs. That’s part of what changed: low-dose CT doesn’t wait for a lump to cause a problem you can feel. It can pick up tiny nodules that would never show up on a chest X-ray—and would never announce themselves with symptoms at this stage.
But the result often isn’t a clean finish line. “Normal” can simply mean “nothing worth acting on today,” and “small nodule” may land you in a short-interval recheck instead of a definite answer. Over time, the real value comes from comparisons: this year versus last year, a spot that stayed the same versus one that changed. The limitation is emotional as much as practical—more detail can mean more watching, not immediate clarity.
Eligibility rules reflect risk, not perfect fairness
You notice it when you start doing the math out loud: two people can smoke for decades and still land on different sides of the “eligible” line. One quit 14 years ago and qualifies; another quit 16 years ago and doesn’t. It can feel arbitrary, especially when both of them still have that familiar morning throat-clearing and neither feels sick. That mismatch is part of the point—and part of the discomfort.
Eligibility rules aren’t trying to sort people into “safe” and “unsafe.” They’re built to catch the group where the chances of finding something meaningful early are high enough to justify years of repeat scans, follow-ups, and the occasional false alarm. Age and pack-years are blunt tools, and they don’t capture everything (like family history, radon exposure, or how your body handled smoke). So the rules aim for risk, not perfect fairness—and sometimes that leaves people feeling unseen on either side of the cutoff.
More findings can create uncertainty, not relief
The waiting often starts before you even read the report. A friend says, “If they don’t call, you’re fine,” and then you open the portal and see a word you weren’t expecting: nodule. It may be described as “tiny” or “likely benign,” yet it can still land like a problem you didn’t have yesterday. That’s the odd emotional math of low-dose CT—more detail can make you feel less settled, even when the practical message is “watch, not worry.”
Part of the uncertainty is that a lung scan doesn’t just look for one thing. It also notices old scarring, inflammation, little spots that could be from past infections, and shadows that are hard to categorize from a single snapshot. A “small nodule” result often isn’t a diagnosis; it’s a request for time and comparison—sometimes a shorter-interval scan to see whether it changes. Your life keeps moving while the answer stays conditional, measured in millimeters and months.
Follow-up pathways quietly drive the detection benefit
Sometimes the next step isn’t dramatic—it’s an appointment that looks almost the same as the first one, just sooner than you expected. A report might say “repeat in 3 months” or “6 months,” and that can feel like a half-answer. But those short-interval rechecks are where screening quietly does its real work: they turn a single blurry snapshot into a trend line. A spot that doesn’t change over time starts to look less urgent; a spot that grows, even a little, becomes harder to ignore.
Some people move from repeat CTs to a specialist visit, a PET scan, or a biopsy; others never need anything beyond routine annual screening. The benefit depends on that stepwise follow-up happening on schedule, even when you feel fine and the language in the report stays cautious instead of certain.
Screening reveals new trade-offs in treatment timing

It’s strange how a “good catch” can still feel like a disruption. You go in expecting reassurance, and instead you’re suddenly talking about timelines: whether something should be watched for a few months, sampled now, or removed before it ever causes a symptom. When a spot is found early, the question isn’t only “Is this cancer?” but also “If it is, how fast do we need to move?”—and the honest answer can be, “It depends,” which is hard to live with.
Earlier detection can pull treatment decisions forward into a part of life where you still feel normal. That can be a relief, but it can also create new trade-offs. Some nodules grow so slowly that immediate surgery might feel like acting on a problem that hadn’t yet become a problem in your body. Other findings may look small but sit in a location that makes waiting feel riskier. Screening doesn’t remove uncertainty—it often shifts it into the timing of the next step, and how much “watching” is enough before doing more.
What’s evolving next in screening and equity
At some point, the hardest part isn’t the scan—it’s realizing how much of the process depends on what happens outside the scanner room. Two people can get the same “small nodule” wording and still experience totally different next steps, simply because one can schedule a 3‑month recheck easily and the other can’t miss work, can’t travel, or can’t afford the added visits. Screening may look like a single annual decision, but in everyday life it behaves more like a chain of appointments, reminders, and follow-through that not everyone can keep equally.
That’s where screening is evolving: not just better images, but better ways to match care to real risk and make the follow-up path easier to finish. Some programs are pushing toward clearer, more consistent reporting, reminders that don’t rely on you remembering, and risk tools that go beyond age and pack-years. These improvements can feel invisible until you’re the one trying to stay on the timeline year after year.